The AI Revolution in Pharma: Remaking Medical Affairs, One Insight at a Time

Authors: Michael Fath, PhD1,2; Gerald L. Klein, MD2; L. Allen Kindman, MD2; Larry Florin, MBA2; Victoria Manax, MD2; Shabnam Vaezzadeh, MD1,2

Affiliations: Cavabio Consulting, LLC1; MedSurgPI, LLC2

The pharmaceutical landscape is witnessing a seismic shift, propelled by rapidly evolving waves of artificial intelligence (AI). AI’s impact on drug discovery and development has been extensively documented, and the implications for Medical Affairs are equally significant. This white paper examines the potential of AI to transform how MA professionals engage with healthcare professionals (HCPs), gather insights, and navigate the ever-evolving healthcare ecosystem.

Artificial Intelligence: What Is It and What Can It Do

AI is an extremely hot topic and nowadays has entered many business discussions as a key driver of future success. It is paramount to have clarity on what it entails and how it can be used. 

In the simplest definition, AI is the science of creating machines that can think similarly to humans and process data in a quantity and speed beyond human capabilities. AI is projected to revolutionize our lives in ways that we cannot yet fully imagine.[1]  AI has transformed many industries already, as its elements, such as reinforcement learning, supervised and unsupervised learning, computer vision, natural language processing and deep learning have been incorporated in different facets of our lives to varying degrees. Chatbots and predictive models have gradually become a routine part of systems interfaces.[2]

AI is predictive and single tasked as opposed to multitasking humans.[2]  AI does have limitations and consequently human interface is required when utilizing the current AI tools such as ChatGPT. 

 Beyond Automation: Unveiling the Data Treasure Trove

Imagine being buried in a sea of data – clinical trial results, real-world evidence, competitor analysis, and mountains of scientific publications. This is the daily reality for many MA professionals. AI, however, can act as a powerful data interpreter, unearthing hidden patterns and correlations that can escape the human eye. Natural language processing (NLP) focuses on the interaction between computers and humans through natural language. In the context of medical affairs, NLP technology plays a crucial role in enhancing the efficiency, accuracy, and depth of various processes and research.  This technology can sift through vast swathes of unstructured text, uncovering trends in HCP conversations, patient feedback, and social media discussions.[3] This real-time intelligence informs MA strategies, allowing for targeted interventions and proactive responses to emerging issues.[4]

Personalized HCP Engagement: From Routine to Resonance

Gone are the days of one-size-fits-all interactions. While not currently commonplace, AI powered chatbots can be developed to handle routine inquiries, freeing up valuable time for MSLs to engage in deeper, more strategic conversations.[5] Personalized content recommendations, tailored to individual HCP’s interests and practice areas, ensure relevant information reaches the right audience.[6] Sentiment analysis tools gauge HCPs' responses during interactions, allowing Medical Science Liaisons (MSLs) to adjust their approach and address specific concerns proactively.[7] This shift from information delivery to insightful dialogue builds trust and strengthens relationships, ultimately leading to better patient care, a key objective for medical affairs.[3]

From Insights to Impact: Optimizing Patient Care & Market Reach

AI's potential extends beyond HCP engagement, directly impacting patient care and market reach. Machine learning algorithms are being developed that can analyze patient data to predict potential adverse events, optimize medication regimens, and identify patients most likely to benefit from specific therapies.[8] This personalized approach has the potential to improve patient outcomes while reducing healthcare costs.[6]  For market insights, AI analyzes competitor analysis, regulatory landscapes, and healthcare policy proposals, predicting future trends and identifying new market opportunities.[3] This forward-looking intelligence allows MA teams to adapt strategies and proactively engage with relevant stakeholders, a crucial aspect of market research.[5]

Challenges and Considerations: The Human Touch Remains Essential

Despite its promise, AI implementation in MA comes with its own set of challenges. Data quality and security are paramount, requiring robust infrastructure and ethical data governance practices.[4] Integration with existing systems and workflows can be complex, necessitating careful planning and training.6 However, the most crucial aspect remains the human element. AI should augment, not replace, the expertise and empathy of MSLs and medical advisors.5 The role of the medical affairs professional becomes more critical, focusing on the interpretation of AI-generated insights, building relationships, and providing human-to-human guidance.

The Future of MA: A Symbiotic Partnership

The future of MA lies in a synergistic partnership between human expertise and AI capabilities. By embracing AI, MA professionals can become more efficient, data-driven, and patient-centric, ultimately improving the value they bring to the healthcare ecosystem. This transformative journey requires ongoing investment in AI literacy, upskilling of MA teams, and a commitment to ethical and responsible AI implementation.3

AI Tools for MA

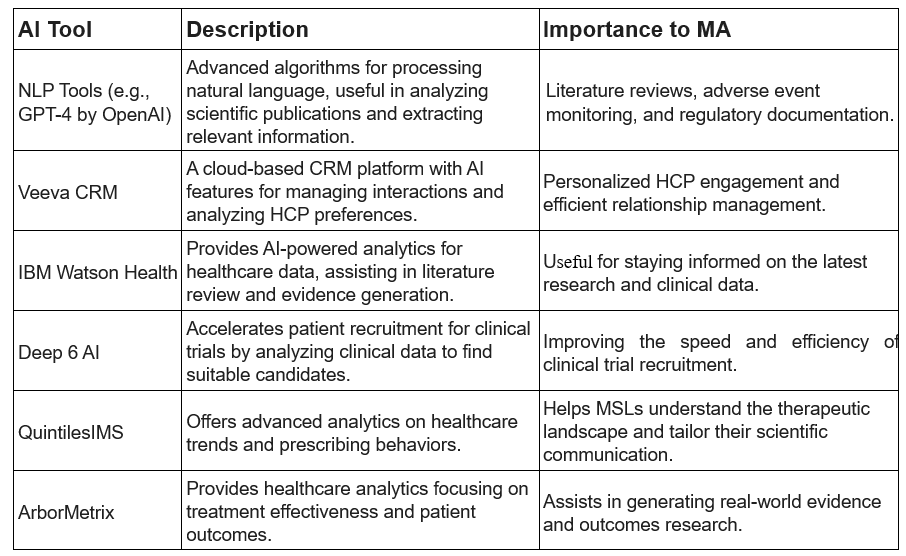
AI tools will be valuable in Medical Affairs so long as these tools support the critical responsibilities of MA while facilitating privacy and compliance aspects. Several Customer Relationship Management (CRM) tools are in the process of incorporating AI tools into their offerings. Stand-alone AI tools are also important options to be evaluated.  Table 1 shows a partial list of some AI options.

 Table 1
Embracing the AI Revolution:

 With its potential to revolutionize HCP engagement, data analysis, and patient care, AI is poised to rewrite the script for Medical Affairs. By navigating its challenges and embracing its opportunities, MA teams can leverage this powerful technology to enhance their impact and drive better healthcare outcomes for patients. This is not just an evolution, it's an AI revolution, and MA professionals are at the forefront, navigating the data tsunami and leading the way toward a future where insights, not information, drive medical breakthroughs and improve lives.

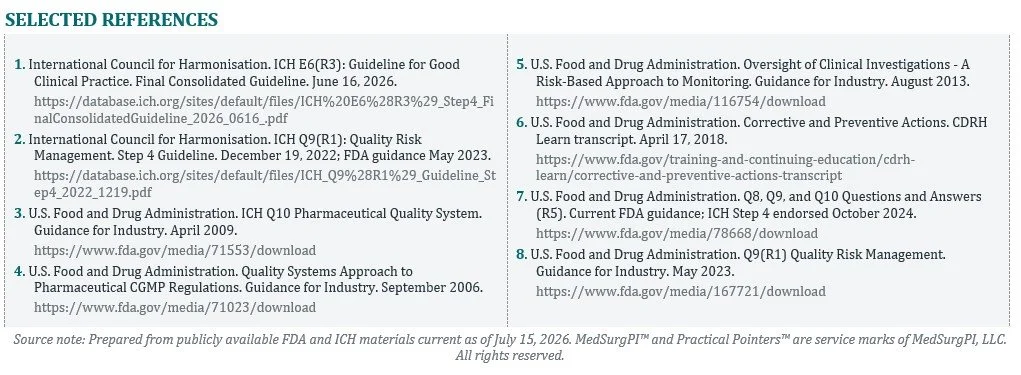
References

 1  HCLTech (2021).  Artificial Intelligence, defined in simple terms (https://www.hcltech.com/blogs/artificial-intelligence-defined-simpleterms#:~:text=Artificial%20intelligence%20is%20the%20science,decisions%2C%20and%20judg e%20like%20humans).

2  World Economic Forum (2023).  What is artificial intelligence – and what is it not?  https://www.weforum.org/agenda/2023/03/what-is-artificial-intelligence-and-what-is-it-not-aimachine-learning/.

3  McKinsey & Company (2023). Unlocking the Value of Medical Affairs.

4  Blue Matter Consulting. Case Studies: AI in Medical Affairs.

5  THE MSL (2023). The Impact of AI on Medical Affairs.

6  Deloitte (2022). AI in Pharma and Life Sciences: Reimagining the Future of Healthcare. https://www2.deloitte.com/us/en/pages/life-sciences-and-health-care/articles/futureof-artificial-intelligence-in-health-care.html.

7  The Impact of AI on Medical Affairs (2022). A white paper by the Medical Affairs Professional Society. https://medicalaffairs.org/wp-content/uploads/2022/09/White-paper-AI-for-MedicalAffairs-rebranded.pdf.

8  Blue Matter Consulting (2021). AI in the Pharma Industry: Transforming Drug Discovery and Development.
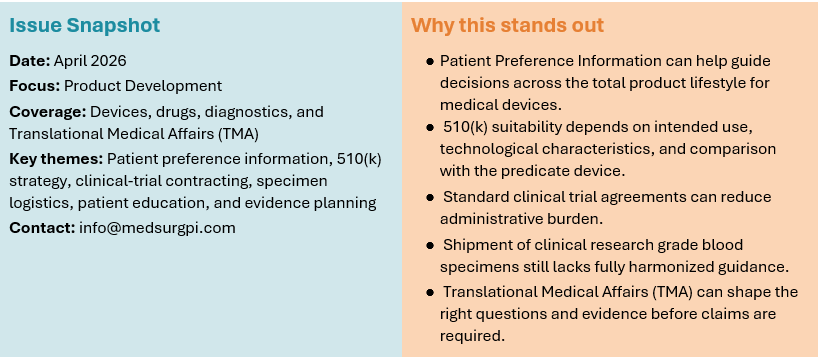
Practical Pointers for Drug Development and Translational Medical Affairs / July 2026

Authors:  Gerald L. Klein, MD [1]; Michael J. Fath, PhD [1,2]; Patrick Loebs, MSW, MPH [1]; Freddy Byrth, BA [1]; Roger Morgan, MD [1]; Shabnam Vaezzadeh, MD [1,3]; Thomas Krol, PharmD [1]

Affiliations: MedSurgPI [1]; Cavabio Consulting [2]; Exquisite Biomedical Consulting [3]

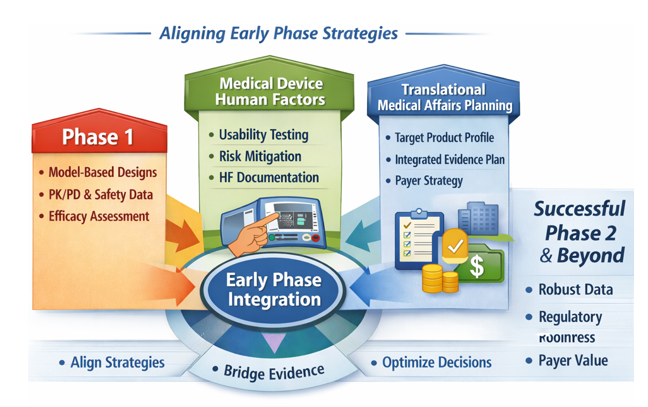
 Drug Development

 Practical Pointer: Use ICH M11 as the default protocol template but map it to regulatory content first.  21 CFR 312.23(a)(6)

The Point: The International Council for Harmonization of Technical Requirements for Pharmaceuticals for Human Use (ICH) M11 is now the first globally harmonized ICH standard for clinical trial protocol structure and electronic exchange. FDA issued the M11 guideline, template, and technical specification as final guidance in May 2026. M11 standardizes structure, numbering, and terminology, and supports machine-readable protocol elements that flow into downstream systems. However, because FDA requires content rather than a specific format, sponsors should map any protocol template to 21 CFR 312.23(a)(6) (for INDs) or 21 CFR 812.25 (for devices) to ensure completeness. M11’s scope is primarily medicinal-product trials, so device-led studies may require additional tailoring. For combination products, the primary mode of action (PMOA) guides the lead center and investigational pathway, and applicable requirements for each constituent part must be addressed.  Where a single application is used, relevant constituent-part requirements should be incorporated as appropriate.

 What to do:

·    Map the template to the regulation: Before drafting, confirm that the protocol addresses every required element in 21 CFR 312.23(a)(6) (for Investigational New Drugs (INDs)) or 21 CFR 812.25 (for devices), including objectives, design, bias controls, dose and duration, assessments, and monitoring. M11 provides structure, but the regulation defines the obligation.

·    Build critical‑to‑quality factors into the protocol and into the organization: ICH E6(R3) treats the protocol as the place where proportionate risk controls and critical‑to‑quality factors are designed in. But E6(R3) goes further: it expects quality to be built prospectively into trial design and conduct, with critical-to-quality factors identified early and their risks managed proportionately throughout the trial. The protocol template is a prompt, not a substitute for organizational behavior, training, governance, and ongoing risk management. So, sponsors must deliberately add these expectations to their templates and train all staff, so they are encoded in behaviors to avoid inconsistent or reactive quality practices later into the trial.

·    Run SPIRIT 2025 as a final completeness cross-check: Standard Protocol Items: Recommendations for Interventional Trials (SPIRIT) 2025 is a reporting guideline, not a template, but it reliably catches gaps that templates miss, including harms assessment, patient involvement, and open-science items. The updated guideline (Chan, AW., Boutron, I., Hopewell, S. et al. SPIRIT 2025 statement: updated guideline for protocols of randomized trials. Nat Med 31, 1784–1792 (2025) https://doi.org/10.1038/s41591-025-03668-w) underscores the importance of documenting rationale and transparency for each protocol element. Use SPIRIT 2025 as a final completeness cross-check. When an item is not applicable, document that explicitly with a brief rationale to preserve reviewer navigation and demonstrate intentional completeness.

·    Determine PMOA for combination products: For products with both drug and device characteristics, confirm the PMOA to determine whether the review will fall under the Center for Drug Evaluation Research (CDER), the Center for Biologics Evaluation and Research (CBER) or by the device center, the Center for Devices and Radiological Health (CDRH). PMOA guides the lead center, and requirements for the constituent parts should be incorporated as appropriate within a unified and filing package.

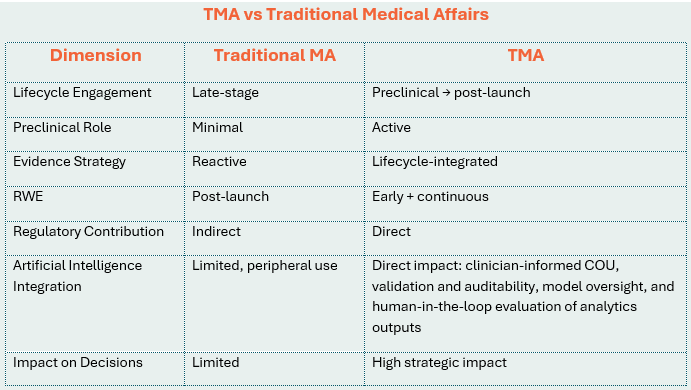
Translational Medical Affairs

 Practical Pointer: Keep reactive off-label responses separate from proactive scientific exchange.

The Point: Medical affairs may respond to unsolicited off‑label questions, but firm‑initiated scientific exchange follows a different, stricter rule set. Compliance risk arises when the lanes blur, especially when a reactive question is converted into proactive communication or when off‑label content appears in promotional channels. The distinction is not about the science itself; it is about who initiated the conversation and where the information lives. The January 2025 Scientific Information on Unapproved Uses (SIUU) guidance as not yet for implementation pending OMB review, so these should be described as FDA recommendations and enforcement-policy considerations rather than requirements. In practice, the dividing line depends on initiation, audience/channel, evidentiary content, required or recommended disclosures, and clear separation from promotion.

 What to do:

 ·    Follow FDA rules for unsolicited requests: For reactive off‑label questions, answer only the specific question asked, respond privately to the requester, keep content truthful, balanced, and non‑promotional, and document both the request and the response. The 2011 FDA draft guidance remains the reference for this lane.

·    Apply the 2025 guidance for proactive scientific exchange: Firm-initiated scientific information on unapproved uses should follow the principles outlined in FDA’s January 2025 SIUU guidance (document ending in 184871), recognizing that FDA currently treats this as enforcement-policy guidance pending OMB review. These communications should rely on scientifically sound publications, include recommended disclosures, and remain fully separate from promotional content in both substance and channel. Use dedicated webpages, emails, and meeting spaces so approved‑use promotion and unapproved use science are not conflated.

 ·    Train Medical Affairs staff to maintain the firewall: Field staff must recognize unsolicited requests, avoid converting them into proactive discussions, and keep medical information response documents balanced and fully referenced. Most compliance failures arise not from possessing off‑label science, but from blurring who initiated the conversation and where the information is stored.

·    Scientific Exchange Considerations: Some factors that should be considered to maintain the firewall between reactive medical information and proactive scientific exchange (to be approved by company management):

o   Regulatory status: The use of [drug name] for [unapproved use] is NOT approved by the FDA.

o   Clinical Status: The safety and efficacy of [drug name] for this indication has not been fully evaluated or established.

o   Approved Use: [drug name] is indicated only for [insert approved indication].

o   Purpose: This information is provided solely as a factual, balanced response to an unsolicited scientific inquiry. It does not constitute medical advice or a promotional recommendation. Please see the attached full [prescribing information / product labeling] for authorized usage guidelines.

o   Tracking: Publications provided to covered recipients should be assessed for reportability under Open Payments requirements and company policy, rather than automatically reported for each healthcare professional.

o   Scientific rigor expectations: For proactive SIUU communications, follow FDA’s recommended principles for evidence-based, non-promotional scientific exchange directed to an appropriate scientific audience, with disclosures consistent with the January 2025 SIUU guidance.

Breaking the CAPA Trap by Adopting a Prevent-First Quality Framework

Why closing more CAPAs is not the same as building a system that fails less often

Authors: Aida P. Carfagno[1], Gerald L. Klein, MD[2]; Shengjun Zhang, MD[3]; Freddy Byrth, BA[2]; David Weinstein, MD, PhD[4]

Affiliations: Cedar and Stone Consulting[1]; MedSurgPI, LLC[2]; BIOTrialMed[3]; David Weinstein Consulting Inc[4]

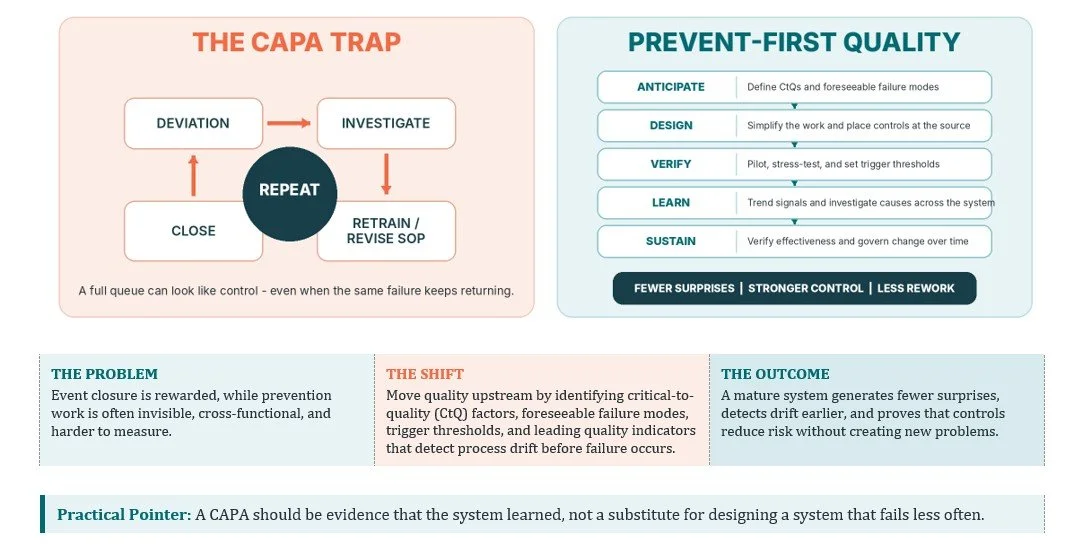
Every Corrective and Preventive Action (CAPA) tells two stories: the problem that occurred and the thinking that allowed it to happen. In many regulated organizations, CAPA has become the place where quality problems go after they happen. Deviations are opened, investigations are written, training is assigned, SOPs are revised, and closure dates are tracked. Months later, there will be an “effectiveness check” to confirm that corrective actions were completed on time. The system looks busy yet produces the same failures repeatedly. The problem isn’t the CAPA process. The problem is relying on CAPA to compensate for weaknesses that should have been prevented through thoughtful process design, effective risk management, and strong operational oversight.

The Prevention Test: Every proposed corrective or preventive action should answer one fundamental question: Will this action make the process more resilient, or will it simply document that we did something? The Prevention Test provides a practical way to distinguish between the two.  If the answer is no, the action may close a CAPA without meaningfully reducing risk or preventing recurrence.

Why Organizations Get Stuck in the CAPA Trap

The recurring problem is usually the operating system, not the quality form.

Nine Warning Signs: Every CAPA process tells a story about how an organization thinks. The health of that process isn't measured by how many investigations are completed or how quickly actions are closed. It's measured by whether the organization is learning, improving, and preventing recurrence. When investigations consistently stop at the obvious, retraining becomes the default answer and recurring issues are accepted as inevitable. The process has stopped driving improvement and started preserving the status quo. If you recognize several of the warning signs below, your CAPA process may be treating symptoms rather than solving problems.

Why the Trap Persists

Closure Pressure: Due dates reward administratively easy actions.

Siloed Signals: Data are not trended across programs, functions, or partners.

QA-Only Ownership: Process owners lack authority or resources to redesign work.

Lagging Metrics: Dashboards count failures and aging, not early warning or control.

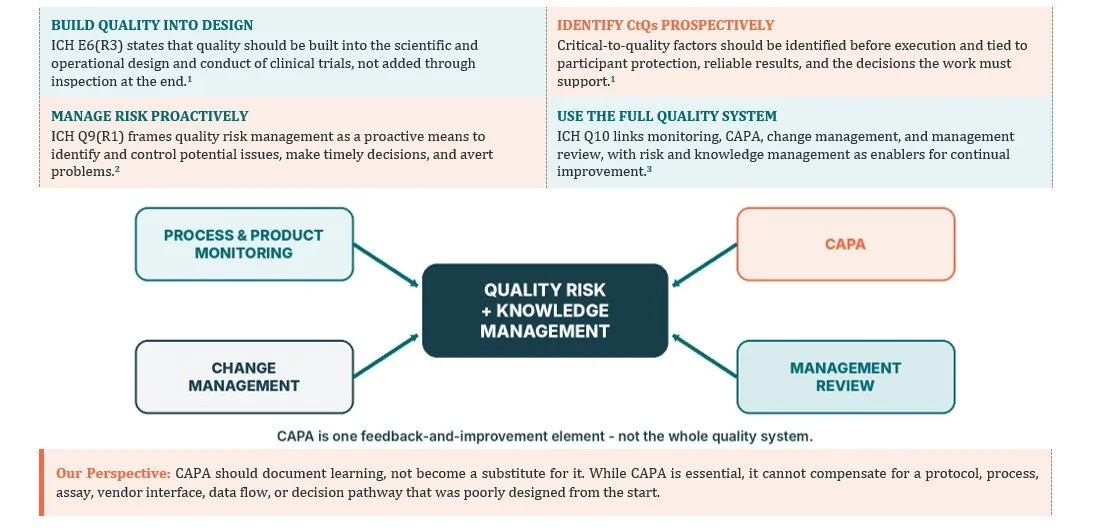
What Current Quality Guidance Points Toward

A Prevention-First Quality Operating Model

Move from event closure to prospective control, early warning, and demonstrated learning.

From Reactive CAPA Habit to a Prevention-First Quality System

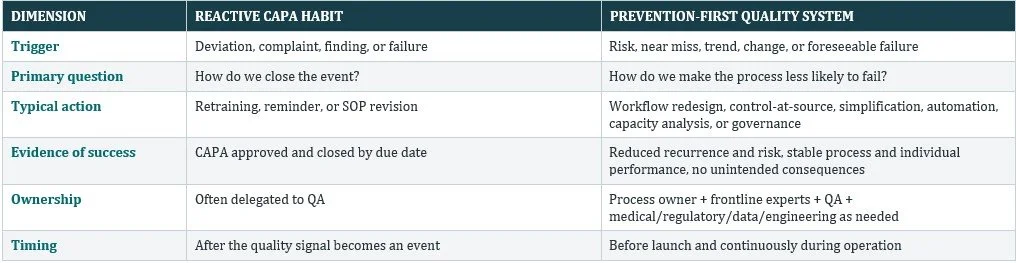
The question isn't whether an organization has a CAPA process. Every mature quality system does. The real question is whether CAPA is driving organizational learning or simply documenting organizational memory. Prevention-first organizations use CAPA as one source of insight within a broader quality system designed to anticipate risk, strengthen processes, and continuously improve. The distinction is not procedural; it is strategic, cultural, and ultimately shaped by leadership. The comparison below illustrates the differences between these two approaches.

Bottom Line: Prevention starts before the deviation occurs. CAPA should convert what the organization learns into better process and product understanding, new or modified controls, verified improvement, and accountability.

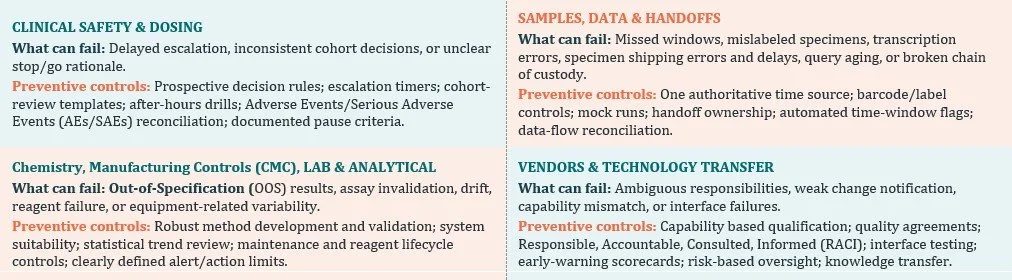
Where Prevention Creates the Most Value

Four High-Value Prevention Domains

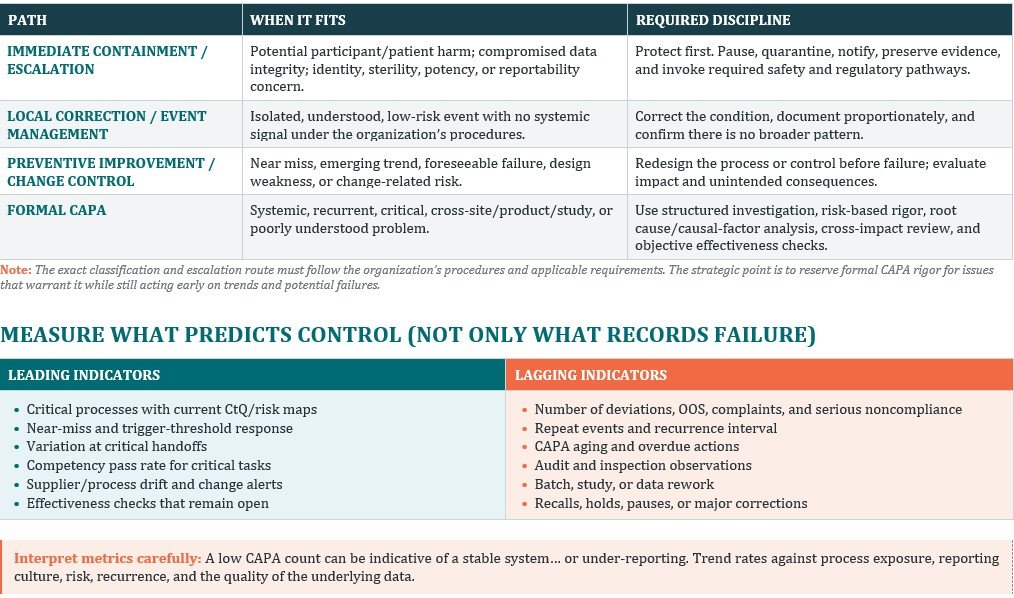
Not Every Problem Requires a CAPA

One hallmark of mature organizations is their ability to distinguish between events that require immediate action, issues that call for process improvement, and problems that demand formal investigation. A prevention-first quality system recognizes that not every event requires the same level of investigation or oversight. Applying the appropriate response - whether immediate containment, local correction, preventive improvement, or formal CAPA - helps organizations address risk efficiently while preserving the rigor of the CAPA process for issues that truly warrant it, thereby focusing resources where they create the greatest value.

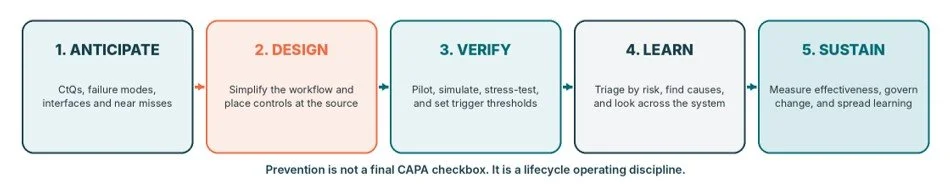
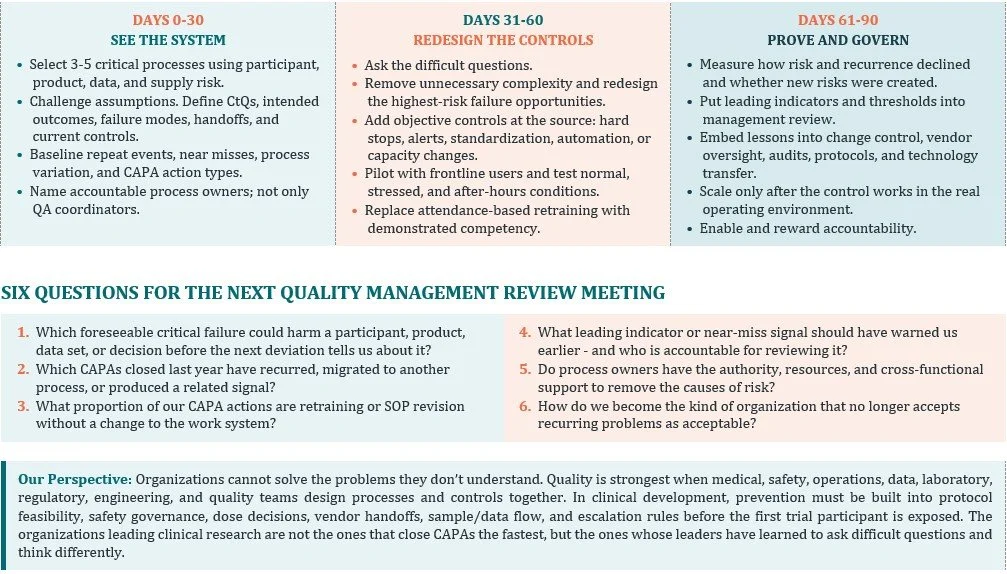
A 90-Day Plan to Break the CAPA Trap

Make prevention visible, owned, measurable, and part of normal operating governance.

MedSurgPI and Cedar and Stone Consulting can help: Quality-by-design reviews | clinical and safety risk mapping | independent readiness assessments and audits | CAPA/root-cause analysis strengthening | medical and regulatory governance

More Physicians and Dentists Should Participate in Clinical Trials

MedSurgPI, LLC is proud to share our editorial: More Physicians and Dentists Should Participate in Clinical Trials Now! This article has been accepted by Cureus. This piece highlights how research involvement can expand patient options, strengthen clinical relevance, and connect everyday practice to emerging science. A sincere thanks to our outstanding coauthors for their expertise, collaboration, and commitment to advancing clinical research across diverse practice settings.

Biobanking: The Hidden Infrastructure Behind Precision Medicine

The East Carolina University (ECU) School of Dental Medicine is building its research enterprise.

This spotlight features a saliva Biobank at the ECU School of Dental Medicine as it builds its research enterprise under Dr. Alexandre R. Vieira, DDS, MS, PhD, Dean for Research

Authors: Gerald L. Klein, MD[1]; Freddy Byrth, BS[1]; Michael Fath, PhD[2]; Aida Carfagno, BS[3]; David Weinstein, MD, PhD[4]; Patrick Loebs, MSW, MSH[1]

Affiliation: MedSurgPI[1]; Cavabio Consulting[2]; Cedar and Stone Consulting[3]; David Weinstein Consulting[4]

Technology Innovation Spotlight features a saliva Biobank at the ECU School of Dental Medicine.   Behind nearly every modern biomarker, companion diagnostic, and target-validation program sits an asset that seldom appears in the press release: well-characterized biospecimens, collected under controlled conditions and linked to longitudinal clinical data. Biobanking, the systematic collection, processing, storage, annotation, and distribution of biological specimens and their associated data, has quietly become one of the most consequential enabling technologies in drug, biologic, device, and diagnostic development. What was once thought of as “a freezer in the basement” is now a data-rich, standards-governed, increasingly automated infrastructure layer for precision medicine. Modern biobanks are therefore not only technical infrastructure; they are also trust infrastructure, dependent on transparent consent, privacy protections, and participant confidence that specimens and data will be used responsibly.
THE OPPORTUNITY

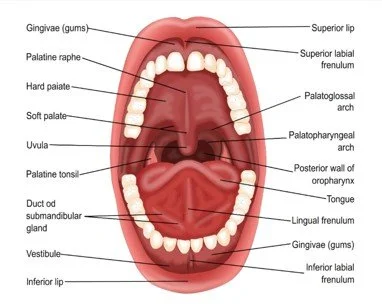
Saliva is among the most practical biofluids for population-scale collection. It can be gathered noninvasively, at low cost, and without specialized phlebotomy, and it carries a rich repertoire of analytes, including cells, nucleic acids, extracellular vesicles, metabolites, and proteins. Because oral and systemic health are increasingly understood to be connected, saliva offers a window not only into caries and periodontal disease but also into systemic conditions, with the added advantage of supporting repeated, longitudinal sampling at minimal patient burden.

THE INNOVATION

The center of gravity in biobanking has shifted from the specimen to the specimen plus the data wrapped around it. Three converging developments explain the change.


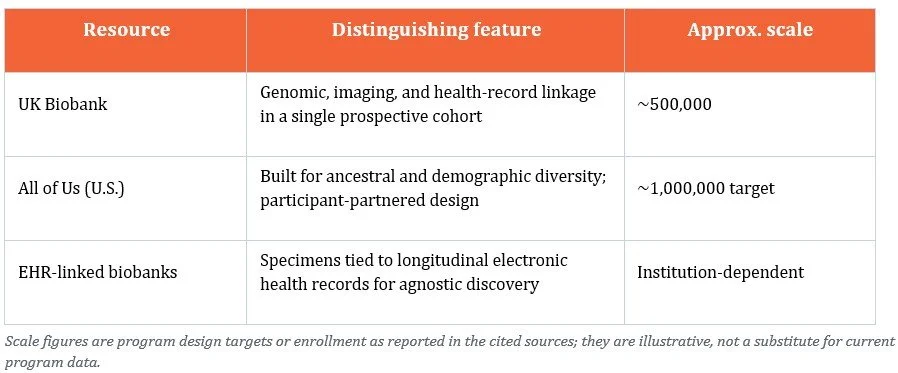
First, scale. Population-scale biobanks now operate at a size that was impractical a decade ago. The UK Biobank enrolled roughly 500,000 participants with linked genomic, imaging, and health-record data,[1] while the U.S. All of Us Research Program was designed explicitly to build a large, diverse cohort that mirrors the populations medicine actually serves.[2]

Second, data linkage. The research value of a biobank today depends heavily on how richly its specimens connect to electronic health records that can be queried in depth; robust phenotyping, and multi-omic readouts. The combination, not the specimen in isolation, is what enables agnostic and unbiased discovery across thousands of associations among diseases, genes, and exposures.[3]

Third, quality as a discipline. Preanalytical variables such as time to processing, freeze and thaw cycles, fixation, and storage temperature can materially alter the molecular characteristics of a sample and, with it, the validity of any downstream result. Reporting frameworks such as BRISQ (Biospecimen Reporting for Improved Study Quality) were created to make those variables transparent and reproducible,[4] and the international standard ISO 20387 now defines general requirements for biobanking competence and consistency.[5] Alongside scale and linkage, this quality science is what turns a collection of tubes into an extensive and rich research asset.

WHY IT MATTERS

•    Noninvasive, low-cost collection enables large, diverse cohorts and repeat sampling that blood-based biobanks struggle to match.

•    Chart-linked saliva supports biomarker discovery for oral conditions such as caries and periodontitis, as well as for systemic disease through the oral-systemic axis.

•    A newer school building its portfolio can design consent scope, quality systems, and annotation for partnering from the outset rather than retrofitting them later.

•    For sponsors, a well-governed saliva resource offers a practical platform for noninvasive biomarkers and companion-diagnostic work.

Representative large-scale biobanks frequently cited as exemplars:

FEATURED EXAMPLE:

Saliva is among the most practical biofluids for population-scale collection. It can be gathered noninvasively, at low cost, and without specialized phlebotomy, and it carries a rich repertoire of analytes, including cells, nucleic acids, extracellular vesicles, metabolites, and proteins. Because oral and systemic health are increasingly understood to be connected, saliva offers a window not only into caries and periodontal disease but also into systemic conditions, with the added advantage of supporting repeated, longitudinal sampling at minimal patient burden. ECU School of Dental Medicine is building its research enterprise under Dr. Alexandre R. Vieira, DDS, MS, PhD, Dean for Research, a dentist and human molecular geneticist whose work emphasizes characterizing patients’ whole health trajectories rather than studying one disease at a time. At his prior institution, Dr. Vieira established a dental-school registry under which patients entering the building were invited to contribute two things: permission to draw data from their records and a saliva sample. That pairing of biological specimen with chart-linked clinical data is the linkage that gives a modern biobank its translational power, and it is the model now being extended at ECU as the school formalizes a research portfolio supported by its Office of  research facilities, including a Basic Science Laboratory, a Vivarium, and a Clinical Research Center.[1]

Why this matters to sponsors and licensees:

·         Specimen quality is a data-quality problem: undocumented preanalytical variables undermine biomarker and companion-diagnostic claims.

·         Consent scope is a gating factor: commercial and future-use permissions determine whether a collection can support a development program.

·         ISO 20387 accreditation and BRISQ-style reporting are now table stakes in diligence, not nice-to-haves.

Diverse, electronic health record-linked cohorts shorten the path from hypothesis to validated, generalizable evidence.

THE COMMERCIAL AND TRANSLATIONAL OPPORTUNITY

Industry licensees and development partners do not value specimens generically. They value fit-for-purpose specimens. Four attributes drive whether a collection is commercially useful: documented provenance and preanalytical history; the depth and accuracy of clinical annotation; the scope of consent (in particular, whether commercial and future unspecified research use is permitted); and quality accreditation against an industry-recognized standard. Fit for purpose also depends on intended use: a collection that is adequate for exploratory biomarker discovery may not be sufficient for clinical validation, companion diagnostic development, or regulatory submission if chain of custody, preanalytical controls, assay validation, consent scope, or population representativeness are incomplete. A technically impressive collection with ambiguous consent or undocumented handling can be commercially unusable, an avoidable and expensive surprise late in a program.

For institutions that hold biobank assets, including universities, academic medical centers, and federal labs, this creates a real partnering opportunity, provided the asset is positioned in the language sponsors evaluate against. That framing is where many otherwise-strong collections under-realize their value.


REGULATORY, ETHICAL, AND QUALITY CONSIDERATIONS

Biobanking sits at the intersection of human-subjects protection, privacy law, and quality systems. In the United States, the revised Common Rule introduced provisions for broad consent covering storage, maintenance, and secondary research use of identifiable specimens and data,[1] while HIPAA governs the handling of protected health information. In the EU, GDPR imposes its own constraints on personal-data processing. Specimens used to support regulated product validation, particularly diagnostic and companion-diagnostic validation, additionally invite FDA scrutiny of provenance, characterization, and fitness for the intended use. Layered on top are quality and competence standards (ISO 20387)  and BRISQ recognized biorepository best practices. The practical takeaway: governance and documentation decisions made at the moment of collection determine, years later, whether a specimen can be used at all.

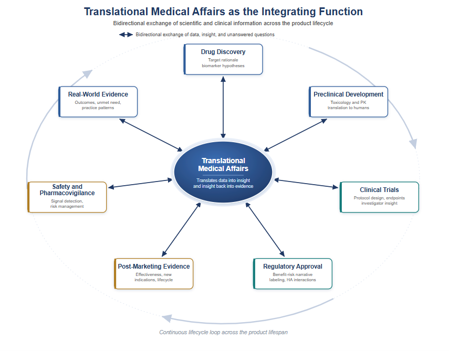
MedSurgPI works at the intersection of clinical development, regulatory strategy, and Translational Medical Affairs, the same intersection where biobank value is won or lost. For institutions and inventors, we translate the science of a collection into the terms industry licensees actually evaluate: provenance, consent scope, fitness for purpose, and the regulatory path the specimens can support. For sponsors, we help define fit-for-purpose specimen and annotation requirements up front, scope consent to the development objective, and avoid the late-stage discovery that a collection cannot support the claim it was meant to enable. Medical Affairs adds particular value by defining the clinically meaningful questions a biobank should answer, identifying KOL and sponsor use cases, shaping evidence‑generation plans, and communicating both the potential and the limitations of the asset transparently.

Practical Pointer

A biobank’s translational ceiling is set at the moment of consent, collections built with commercial and future-use permissions from day one avoid the costly retrofitting that sidelines otherwise strong assets.

[1] Office for Human Research Protections, US Department of Health and Human Services. Federal Policy for the Protection of Human Subjects; Final Rule. Fed Regist. 2017;82(12):7149-7274. Codified at 45 CFR part 46.

[2] East Carolina University School of Dental Medicine. Research. Accessed June 9, 2026. https://dental.ecu.edu/research-department/

[3] Sudlow C, Gallacher J, Allen N, Beral V, Burton P, Danesh J, Downey P, Elliott P, Green J, Landray M, Liu B, Matthews P, Ong G, Pell J, Silman A, Young A, Sprosen T, Peakman T, Collins R. UK Biobank: an open access resource for identifying the causes of a wide range of complex diseases of middle and old age. PLoS Med. 2015;12(3):e1001779. doi:10.1371/journal.pmed.1001779.

[4] All of Us Research Program Investigators. The “All of Us” Research Program. N Engl J Med. 2019;381(7):668-676. doi:10.1056/NEJMsr1809937.

[5] Beesley LJ, Salvatore M, Fritsche LG, Pandit A, Rao A, Brummett C, Willer CJ, Lisabeth LD, Mukherjee B. The emerging landscape of health research based on biobanks linked to electronic health records: existing resources, statistical challenges, and potential opportunities. Stat Med. 2020;39(6):773-800. doi:10.1002/sim.8445.

[6] Moore HM, Kelly AB, Jewell SD, McShane LM, Clark DP, Greenspan R, Hayes DF, Hainaut P, Kim P, Mansfield E, Potapova O, Riegman P, Rubinstein Y, Seijo E, Somiari S, Watson P, Weier HU, Zhu C, Vaught J. Biospecimen reporting for improved study quality (BRISQ). J Proteome Res. 2011;10(8):3429-3438. doi:10.1021/pr200021n.

[7] International Organization for Standardization. ISO 20387:2018. Biotechnology, Biobanking, General Requirements for Biobanking. Geneva, Switzerland: International Organization for Standardization; 2018.

Practical Pointers / June 2026

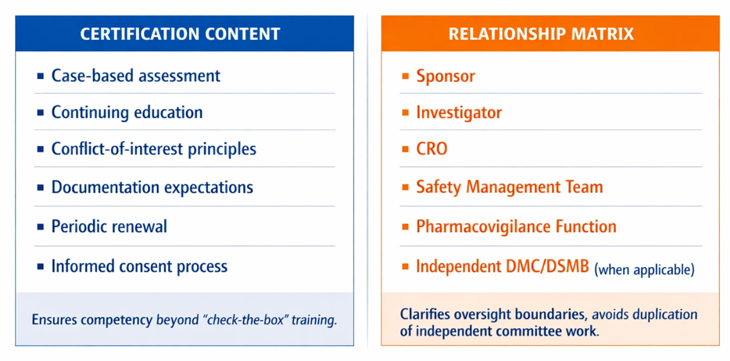
Confirming a Participant Truly Understands the Informed Consent Form Before Signing

Authors:  Gerald L. Klein, MD1; Melissa Palmer2; Freddy Byrth, BA1; Michael Fath, PhD3

Affiliations: MedSurgPI1; Liver Consulting, LLC2; Cavabio Consulting3

Drug Development

The Point: Consent is meaningful only when participants understand it. Since disclosure does not guarantee comprehension, coordinators must verify both decisional capacity and understanding of the specific study before allowing anyone to sign.

A signature on an informed consent form (ICF) documents that disclosure occurred, but it does not prove the participant understood what they agreed to. It is an important ethical and regulatory obligation in clinical research and simply asking, "Do you have any questions?" is not sufficient to confirm comprehension. International oncology trials repeatedly show that most participants cannot correctly answer basic questions about efficacy, risks, and alternatives even after signing.[1] Determining whether someone truly understands the ICF, and therefore whether they should proceed to enrollment requires two separate checks. First, assess decisional capacity: the ability to understand, appreciate, reason about, and express a choice regarding participation. Second, assess comprehension of the specific protocol. Appropriate education, documentation, and, when needed, Institutional Review Board (IRB) approved procedures for a legally authorized representative or additional capacity assessment should support both steps.

A practical two-step approach lets a coordinator or investigator make this determination in a few minutes. First, screen decisional capacity with the University of California, San Diego (UCSD) Brief Assessment of Capacity to Consent (UBACC), a validated 10-item instrument scored 0 to 2 per item (0 to 20 total) that takes under five minutes to administer and, at a threshold score of 14.5, flags participants who warrant more thorough capacity assessment or remediation before enrollment.[2] To support compliance, sites should document the participant’s teach-back responses, any remediation provided, and the basis for concluding that adequate understanding was achieved; without this documentation, a site may perform the right steps but be unable to demonstrate them during monitoring, inspection, or later dispute. Second, confirm comprehension of the actual study using a short teach-back set such as the nine questions which were developed by Klein et al.[3] These questions address the purpose of the study, potential benefits, side effects, procedures, visit burden, participant responsibilities, payment, cost of care for a study-related injury, effect of nonparticipation on usual care, and any out-of-pocket costs. To apply these questions effectively, ask the participant to respond in their own words rather than yes or no.1 Anyone who cannot answer correctly should be re-educated and re-tested, and only those who then demonstrate understanding should be allowed to sign. Building both steps into the consent workflow, and pilot-testing the ICF and questions on lay readers beforehand, protects vulnerable participants without excluding them.

Time the Nonclinical Program to the Clinical Plan, Not to a Checklist

A common and costly error is treating the nonclinical safety package as a fixed checklist rather than a set of studies timed to specific clinical milestones. ICH M3(R2) ties the required duration of repeat-dose toxicity studies to the intended duration of clinical dosing: first-in-human and short trials are supported by short repeat-dose studies of corresponding length, while clinical dosing of six months or longer generally requires a six-month rodent and a nine-month non-rodent chronic dosing study.[4] Before the first-in-human trial, the nonclinical package must also include the safety pharmacology core battery covering cardiovascular, respiratory, and central nervous system function, with dedicated assessment of ventricular repolarization and QT prolongation.[5] It must also include genotoxicity screening that begins with a gene mutation assay and expands to the full battery before larger or longer trials,[6] plus adequate toxicokinetic and general toxicology data. Reproductive and developmental toxicity and carcinogenicity studies are staged later; they gate specific populations and marketing rather than early trials.  

Practical Pointer: at program start, map each nonclinical study to the specific clinical milestone it enables, recognizing that gating requirements vary by intended population, dosing duration, therapeutic area, modality, and regional expectations. This keeps an otherwise clean molecule from stalling simply because a study needed for a particular cohort wasn’t initiated in time.

Devices

Use a Predetermined Change Control Plan to update an AI-enabled device without a new submission

The Point: If your device includes an artificial intelligence-enabled software function that you expect to retrain or refine after authorization, a Predetermined Change Control Plan (PCCP) lets you pre-specify and pre-authorize those changes in your original marketing submission, so you can implement them later without a new 510(k), De Novo, or premarket approval submission.  

The FDA’s final guidance issued on 18 August 2025 establishes the framework for PCCPs for AI-enabled device software functions across the 510(k), De Novo, and PMA pathways. The guidance defines three required components: a Description of Modifications that states the changes the manufacturer intends to make, a Modification Protocol that details how each change will be developed, validated, and implemented, and an Impact Assessment that evaluates the effect of the changes on safety and effectiveness. PCCPs are reviewed as part of the marketing submission, and modifications that fall within an approved plan may be implemented without a new submission.[1]

What to do. Keep the plan focused and verifiable, risk-based, evidence-based, transparent, and lifecycle-oriented, in line with the joint FDA, Health Canada, and Medicines and Healthcare products Regulatory Agency guiding principles.[2] Raise the plan early with the review division through a pre-submission, address labeling so users know the device was authorized with such a plan, and do not attempt to include changes to the intended use, which sit outside these plans and still require a new submission. A well-scoped plan converts a series of expensive, sequential submissions into one, and is often the most valuable planning step for a device that will keep learning after it reaches the market.

Practical Pointer: Keep your PCCP narrowly scoped, evidence-based, and transparent, raise it early through a pre-submission, and avoid including intended-use changes, which always require a new submission.

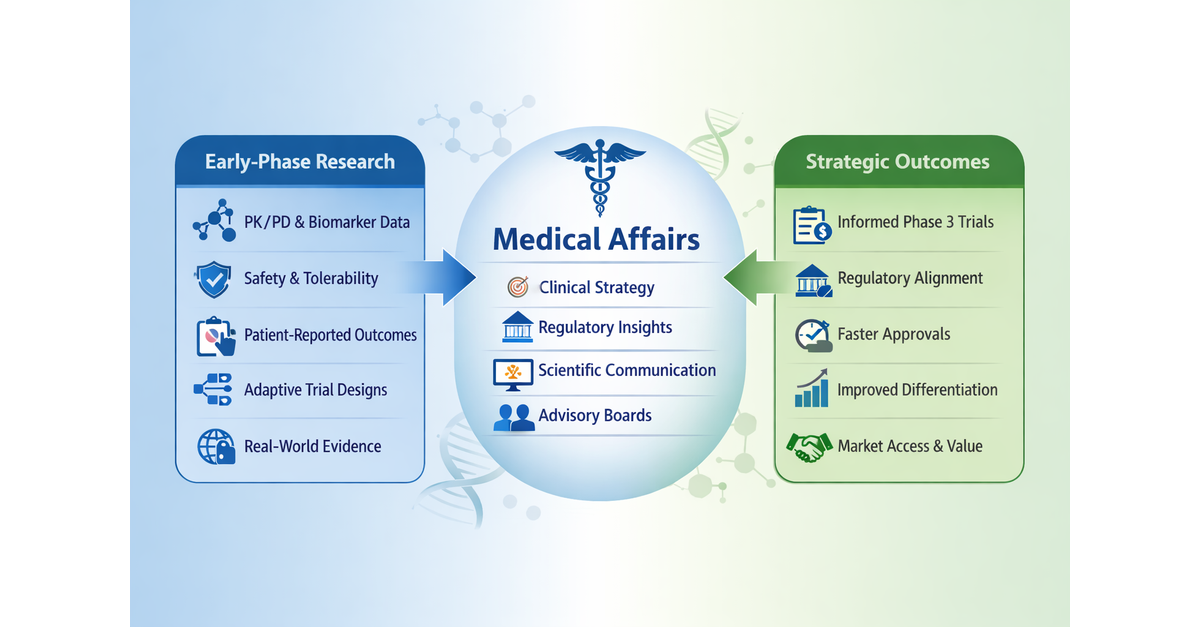
Medical Affairs

Keep the line clear between answering an off-label question and initiating one. 

The Point:  Medical affairs may respond to an unsolicited request for off-label information, but the rules for firm-initiated scientific exchange are separate and stricter. Treat the two as distinct lanes and never let one drift into the other.


For the reactive lane, the FDA guidance on responding to unsolicited requests remains the reference. Answer only the specific question asked, respond privately to the person who asked rather than broadcasting, keep the information truthful, balanced, non-promotional, and science-based, generate it through medical or scientific personnel, never through the sales force, and document the request and the response.[1]

In the proactive lane, the FDA’s January 2025 final Level 1 guidance on firm‑initiated scientific communications for unapproved uses sets a high bar: source publications must be scientifically sound, required disclosures must accompany the communication, and all materials must remain clearly separated from promotional content, both in substance and in channel, using dedicated webpages, emails, and meeting spaces. In contrast, the reactive lane continues to be governed by the FDA’s 2011 draft guidance on responding to unsolicited requests, which permits manufacturers to provide balanced, non-promotional scientific information when the healthcare professional initiates the inquiry. Distinguishing these two lanes is essential: proactive communications must follow the 2025 framework, while reactive responses must follow the 2011 draft. In practice, this means training medical science liaisons (MSLs) to recognize and preserve an unsolicited request rather than converting it into a proactive pitch, keeping medical information responses balanced and fully referenced, and maintaining the firewall in both content and distribution pathways. The compliance risk rarely lies in possessing off-label science; it lies in blurring who initiated the conversation and where that information is housed.

Practical Pointer: Train MSLs to preserve unsolicited requests exactly as received, keep proactive scientific communications in dedicated non-promotional channels, and document both the request and the response so the lane distinction is always visible.

Publications

Build Good Publication Practice (GPP) 2022 and International Committee of Medical Journal Editors (ICMJE) authorship into the publication plan, not the final draft 

Publication integrity failures, guest authorship, ghostwriting, undisclosed conflicts are almost always baked in at the planning stage. Applying GPP and ICMJE authorship criteria early prevents these problems at a fraction of the cost of repairing them later. 

When teams establish clear roles, require transparent disclosures, and document decisions rigorously from the outset, they eliminate the conditions that allow integrity issues to take root, One practical safeguard is to require an authorship/contribution table at project kickoff and update it at each draft milestone; GPP 2022 explicitly adopts ICMJE criteria as the default and emphasizes that named authors are accountable for data integrity, so the planning process should make that accountability visible from the start. 

MedSurgPI: Elevating Medical and Scientific Communication

MedSurgPI advances the practices described in this paper, clear scientific communication, transparent authorship, disciplined lane management, and responsible innovation.  By supporting teams correctly from the start, MedSurgPI helps organizations build credible, compliant, and scientifically sound materials that stand up to scrutiny.


[1] Nusbaum L, Douglas B, Damus K, Paasche-Orlow M, Estrella-Luna N. Communicating Risks and Benefits in Informed Consent for Research: A Qualitative Study. Glob Qual Nurs Res. 2017 Sep 20;4:2333393617732017. doi: 10.1177/2333393617732017. PMID: 28975139; PMCID: PMC5613795

[2] Jeste DV, Palmer BW, Appelbaum PS, Golshan S, Glorioso D, Dunn LB, Kim K, Meeks T, Kraemer HC. A new brief instrument for assessing decisional capacity for clinical research. Arch Gen Psychiatry. 2007;64(8):966-974. doi:10.1001/archpsyc.64.8.966.

[3] Klein G, Morgan R, Zhang, S, et al. Improving Informed Consent Forms (ICFs) in Clinical Trials, Especially for Vulnerable Populations, A Global Need. Presented at: Society of Clinical Research Associates [SOCRA] Annual Conference; September 28-30, 2023; Montreal Canada

[4] International Council for Harmonisation of Technical Requirements for Pharmaceuticals for Human Use. ICH Harmonised Tripartite Guideline M3(R2): Guidance on Nonclinical Safety Studies for the Conduct of Human Clinical Trials and Marketing Authorization for Pharmaceuticals. Geneva, Switzerland: ICH; 2009.

[5] International Council for Harmonisation of Technical Requirements for Pharmaceuticals for Human Use. ICH Harmonised Tripartite Guideline S7A: Safety Pharmacology Studies for Human Pharmaceuticals. Geneva, Switzerland: ICH; 2000.

[6] International Council for Harmonisation of Technical Requirements for Pharmaceuticals for Human Use. ICH Harmonised Tripartite Guideline S2(R1): Guidance on Genotoxicity Testing and Data Interpretation for Pharmaceuticals Intended for Human Use. Geneva, Switzerland: ICH; 2011.

 [7] US Food and Drug Administration. Marketing Submission Recommendations for a Predetermined Change Control Plan for Artificial Intelligence-Enabled Device Software Functions: Guidance for Industry and Food and Drug Administration Staff. Silver Spring, MD: US Food and Drug Administration; December 2024. Accessed July 2, 2026. https://www.fda.gov/regulatory-information/search-fda-guidance-documents/marketing-submission-recommendations-predetermined-change-control-plan-artificial-intelligence

 [8] US Food and Drug Administration, Health Canada, Medicines and Healthcare products Regulatory Agency. Predetermined Change Control Plans for Machine Learning-Enabled Medical Devices: Guiding Principles. Silver Spring, MD: US Food and Drug Administration; 2025. Accessed July 2, 2026. https://www.fda.gov/medical-devices/software-medical-device-samd/predetermined-change-control-plans-machine-learning-enabled-medical-devices-guiding-principles

[9] US Food and Drug Administration. Responding to Unsolicited Requests for Off-Label Information About Prescription Drugs and Medical Devices: Draft Guidance for Industry. Silver Spring, MD: US Food and Drug Administration; December 2011. Accessed July 2, 2026. https://www.fda.gov/regulatory-information/search-fda-guidance-documents/responding-unsolicited-requests-label-information-about-prescription-drugs-and-medical-devices